
GammaTile reduced surgical bed recurrence and improved overall survival versus postoperative SRT in the Phase 3 ROADS trial of operable brain metastases
Written By: Aasritha Thippavajjala, PharmD
Reviewed By: Pharmacally Editorial Team
GT Medical Technologies reported results from the randomized, multicenter Phase 3 ROADS trial, published as a Rapid Communication in the Journal of Clinical Oncology (JCO), the official journal of the American Society of Clinical Oncology. The study found that surgery followed by GammaTile cesium-131 tile-based radiation therapy (TBRT) reduced surgical bed recurrence and improved overall survival compared with surgery followed by postoperative stereotactic radiation therapy (SRT) in patients with newly diagnosed operable brain metastases.
GammaTile Delivers Stronger Local Tumor Control
ROADS randomized 230 patients with operable brain metastases across 32 centers to either tumor resection plus GammaTile or resection followed by postoperative SRT. The trial evaluated local tumor control and surgical bed recurrence-free outcomes as co-primary endpoints.
At 12 months, the cumulative incidence of surgical bed recurrence was 1.3% with GammaTile versus 15.4% with standard postoperative SRT. GammaTile reduced the risk of surgical bed recurrence by 93%, with a hazard ratio (HR) of 0.07 (95% CI, 0.01–0.56; p=0.012). The 12-month local tumor control rate was 98.7% with GammaTile compared with 84.6% for standard care.
GammaTile also reduced the combined risk of tumor recurrence or death by more than 50% (HR, 0.48; 95% CI, 0.30–0.76; p=0.002).
Overall Survival Was Longer with GammaTile
Overall survival, a key secondary endpoint, also favored GammaTile. Median overall survival reached 42.5 months compared with 17.6 months for standard care, corresponding to a 41% reduction in the risk of death (HR, 0.59; 95% CI, 0.37–0.96; p=0.032).
The safety profile was comparable between treatment groups. Grade 3 or higher treatment-related adverse events occurred in 20.0% of patients receiving GammaTile and 21.7% receiving standard care. Functional status, quality of life, distant brain failure, leptomeningeal disease, adverse events, and radiation necrosis were also similar between groups.
An exploratory composite analysis further showed that GammaTile reduced the combined risk of tumor recurrence or radiation necrosis by 72% (HR, 0.28; 95% CI, 0.12–0.66; p=0.004).
Radiation Begins During Surgery
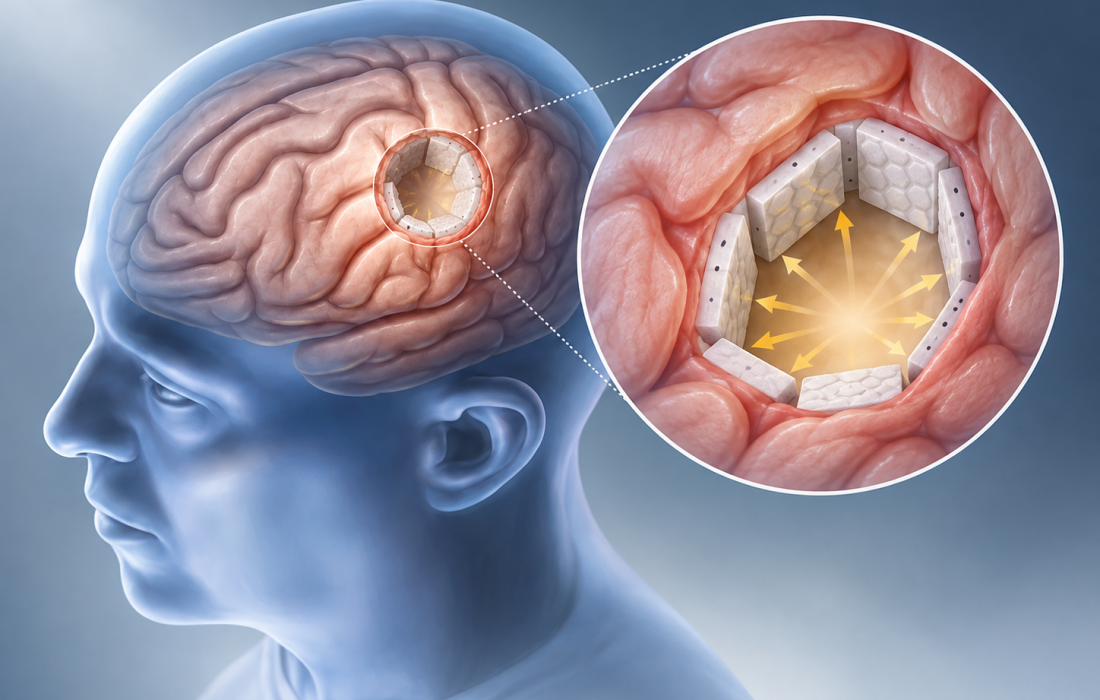
GammaTile is a bioabsorbable collagen implant containing four cesium-131 radiation sources. Surgeons place the approximately 2 × 2 cm tiles directly along the resection cavity immediately after tumor removal. The sources deliver low-dose-rate radiation over several weeks, concentrating treatment at the surgical bed while limiting exposure to surrounding healthy brain tissue.
This approach also addresses a limitation of postoperative SRT, which typically begins weeks after surgery. In ROADS, 17.8% of patients assigned to standard care did not receive their prescribed postoperative SRT. Importantly, GammaTile remained superior in analyses limited to patients who received their assigned radiation, indicating that the benefit was not explained solely by treatment completion.
Authors Support GammaTile as a Standard-of-Care Option
The ROADS investigators concluded that GammaTile should be considered a standard-of-care option for newly diagnosed brain metastases, citing its superiority across both co-primary endpoints without increased radiation necrosis, neurocognitive decline, or deterioration in quality of life.
The publication received Rapid Communication status from JCO, a designation used for findings considered sufficiently significant for accelerated publication. GammaTile is already FDA-cleared for newly diagnosed malignant and recurrent brain tumors, and the company said it has been adopted at more than 150 U.S. centers.
GT Medical Technologies also highlighted the ongoing BRIDGES Phase 3 trial evaluating GammaTile in newly diagnosed glioblastoma, expanding clinical development of the technology into another major brain tumor setting.
Reference
Publication of ROADS Phase 3 Clinical Trial Data in Journal of Clinical Oncology Recommends GammaTile® as a New Standard-of-Care Option for Newly Diagnosed Operable Brain Metastases1, GT Medical Technologies, 29 September 2026
A Phase III Randomized Trial of Surgery with GammaTile vs. Surgery with Standard of Care Radiation for Newly Diagnosed Brain Metastases (ROADS), ClinicalTrials.gov ID NCT04365374
Weinberg JS, Imber BS, DiNapoli V, et al. Surgery and tile-based radiation therapy versus surgery and stereotactic radiation for newly diagnosed brain metastases (ROADS): a randomized, open-label, phase 3 trial. J Clin Oncol. 2026. DOI: 10.1200/JCO-26-01894

About the Writer
Aasritha Thippavajjala (Linkedin) is a pharm D student and aspiring medical writer with medical writing, clinical training experience and a strong interest in clinical research and patient safety She has hands-on exposure to clinical pharmacy activities including medication profile assessment, clinical case review, identification of potential drug-related problems, ADR awareness, patient counselling, and clinical documentation. She has also gained experience in medical literature review, evidence synthesis, and scientific communication through her published review article on digital twin-based patient simulation and her poster presentation at the 74th Indian Pharmaceutical Congress. Certified in ICH Good Clinical Practice (E6(R3)) and Scientific Writing in Health Research, she is passionate about applying her clinical knowledge and research skills to medical writing ,clinical research and contributing to accurate, evidence-based healthcare